

Choosing between an electric vs manual hospital bed should not begin with the assumption that electric is always better or that manual is always more economical. The more useful comparison starts with the actual bed structure and the way each adjustment is produced. An electric hospital bed uses powered actuators and controls to move sections of the mattress platform. A manual hospital bed performs similar basic movements through mechanical crank systems. Both designs can provide backrest and leg adjustment, while selected manual and electric configurations can also provide overall height adjustment. The important differences appear in how frequently those functions are used, how quickly caregivers need to change positions, how many movements the ward requires and how much electrical complexity is appropriate for the application. Hospital procurement teams and distributors comparing electric and manual hospital bed models should therefore compare the mechanisms function by function rather than making the decision from the words “electric” and “manual” alone. Before comparing the drive systems, buyers should define the required patient-platform movements. A general hospital bed may need to provide backrest adjustment and leg adjustment. Some wards also require overall height adjustment. Higher-function electric models may additionally provide whole-bed positioning such as Trendelenburg and reverse Trendelenburg. This means the first question is not whether the bed should have motors. The first question is which physical movements the hospital actually needs. The terms “manual” and “electric” explain how the adjustable sections are moved. A manual bed normally uses crank mechanisms connected to mechanical linkages underneath the mattress platform. The caregiver turns the crank, and rotational movement is converted into movement of the backrest, leg section or complete bed platform depending on the model. An electric bed normally uses linear actuators connected to a control system. The user presses a handset or another approved control interface, and the actuator extends or retracts to change the position of the bed. A common misconception is that electric and manual beds must use completely different sleeping surfaces. In reality, both product types can use articulated platforms divided into several sections. The main difference is how force reaches those sections. Backrest adjustment is one of the most frequently used hospital-bed movements. Depending on the selected model, the backrest may reach approximately 70–75°. Both manual and electric beds can provide this movement. On a manual hospital bed, the caregiver turns the crank associated with the backrest mechanism. The crank transfers movement through a mechanical screw or linkage system, gradually raising the upper mattress platform. The caregiver stops turning when the desired angle is reached. An electric bed replaces repeated crank operation with a powered actuator. The user presses the backrest button and the actuator changes the platform angle. Intermediate positions can be selected by stopping the movement at the required point. Suppose a manual bed and an electric bed both reach approximately 75°. The final position may look similar, but the operating experience is different. Buyers should compare how often staff will need to create that position during a normal day. If the backrest is changed only occasionally, a manual crank may be perfectly practical. If the backrest is adjusted repeatedly throughout every shift, electric control can reduce repeated manual operation. This distinction becomes even more important when several functions are adjusted frequently. Depending on model, the leg section may adjust approximately 30–45°. A manual model creates the movement mechanically. An electric model creates it through an actuator. The useful comparison is not only maximum angle but also frequency of adjustment. Patients are not always positioned with only one section raised. A caregiver may raise the backrest and then adjust the knee section to create a different articulated mattress shape. On a manual bed, this may require operating two separate cranks. On an electric model, the same two functions can be controlled through separate handset buttons. One manual adjustment is simple. Several adjustments repeated many times each day create a different workflow. Buyers should therefore think in terms of total daily adjustments rather than evaluating one demonstration in a showroom. Raising the complete mattress platform requires movement of a much larger part of the bed than raising only the backrest. Both manual and electric height-adjustable beds are available depending on model. A manual three-crank hospital bed can typically allocate its three mechanisms to: backrest adjustment, leg adjustment and overall height adjustment. Depending on the exact model, a manual three-crank bed may provide an example height range around 450–730 mm. The confirmed range should always be taken from the selected model specification. On an electric three-function or five-function hospital bed, height adjustment is normally powered through an actuator and lifting linkage. This changes the caregiver experience because the complete bed can be raised or lowered through the control system instead of a mechanical crank. The easier a function is to operate, the more realistic it becomes to use it repeatedly. For example, staff may lower the bed for one activity and raise it again for another caregiver task. If each change requires repeated manual cranking, staff may naturally use the height function less often. A ward where bed height changes infrequently may not gain enough practical benefit from electric operation to justify additional complexity. This is why usage frequency should remain central to product selection. “Manual hospital bed” describes a broad product category. A two-crank bed and a three-crank bed do not provide the same function set. A typical configuration focuses on backrest and leg adjustment. A typical configuration adds overall height adjustment. Manufacturers can use slightly different descriptions, so the technical datasheet should clearly identify what each crank controls. Buyers should not approve a product based only on the phrase “three-crank.” A common electric three-function configuration includes backrest, leg and height adjustment. But buyers should still confirm the actual movements of the selected model. Depending on design, a five-function electric hospital bed may provide: backrest adjustment, leg adjustment, height adjustment, Trendelenburg and reverse Trendelenburg. This creates a much larger positioning range than a basic manual two-crank bed. When comparing electric and manual beds, buyers should avoid comparing a five-function electric ICU-style bed directly against the simplest manual model and concluding that the difference is only the motors. The function sets themselves are different. A better evaluation compares products with similar intended tasks. For example, compare a manual three-crank model with an electric three-function model when both provide back, leg and height adjustment. Then the real differences in operating method become much clearer. Manual beds depend on mechanical transmission systems rather than electric actuators. The crank mechanism needs to convert repeated hand rotation into controlled platform movement. Operate every crank through its complete range. Check whether movement remains smooth and whether the handle folds or stores correctly according to the product design. The crank should not feel excessively loose or require irregular force during normal operation. The visible handle is only the user interface. Underneath the bed, buyers should inspect the actual mechanical movement. Important areas include screw mechanisms, linkage arms, pivot points, brackets and frame connections. Its quality cannot be judged simply by how shiny the crank handle looks. The linkage geometry and connection points determine how well the function operates. A typical electric adjustment system can include an actuator, control box, handset, cables and power connection. These components create easier operation but also make the product electrically more complex. Buyers should not compare two electric beds only by motor brand. The actuator still needs correctly designed mounting brackets and mechanical linkage. A strong actuator connected to a poorly aligned structure will not produce a good bed. When the motor moves the backrest or lifting frame, force is transferred through relatively small mounting areas. Inspect bracket welding, pivot pins, alignment and connection to the main steel structure. The control box receives commands from the user interface and operates the appropriate actuator. On beds with several powered movements, the electrical architecture becomes increasingly important. Electric operation allows movements to be selected without reaching the foot-end crank area. A practical handset should have clear symbols and logical button grouping. This question affects the value of electric control. If all adjustments are performed by trained staff, either manual or electric operation can be considered depending on workflow. If selected adjustments are intended to be available directly to the patient according to the bed configuration, electric controls can change how the product is used. The crank is normally located where staff access it. This naturally places most adjustment responsibility with the caregiver. Depending on model, control can be provided through a handset or additional caregiver interfaces. Higher-level beds may use side-rail controls or nurse-control systems. These are model-specific features and should not be assumed on every electric bed. More electronics can add useful functions, but they also add components that need to remain compatible and serviceable. Buyers should consider whether the ward actually requires those additional controls. A fully manual hospital bed does not depend on powered actuators for its basic adjustment functions. This can simplify the internal system. Manual does not mean maintenance-free. Crank mechanisms, screws, pivots, linkages, casters, brakes and side rails remain mechanical components that can wear or loosen over time. Adding motors does not eliminate pivots, hinges or steel linkages. Electric beds therefore combine electrical and mechanical systems. A hospital bed needs a stable steel structure whether it is electric or manual. Depending on model, main frames may use rectangular tubing around 80 × 40 mm with wall thickness selected for the particular design. The exact frame specification should be confirmed for the model being evaluated. Some buyers associate electric beds with strength because they look more complex. That is not a reliable way to evaluate structure. A manual bed can use a robust steel chassis and provide a substantial safe working load. Its motors describe how functions are powered, not how strong the complete chassis is. Structural rating should be evaluated separately. Depending on the exact hospital-bed model, safe working load may be 260 kg or higher. The confirmed rating for the selected product should always be used rather than applying one number to all manual and electric beds. Whether the bed is powered or manual, the patient load is ultimately carried through the mattress platform, frame, lower chassis, caster mounts and casters. The structural load path and adjustment drive system are related but different parts of the product. An articulated hospital bed needs a mattress that can follow its moving platform. This requirement does not disappear because the bed is manually adjusted. Bed external dimensions and mattress dimensions are not the same. For example, a hospital bed may have an external width around 960 mm while using a mattress around 900 mm wide depending on model. Buyers should confirm the actual platform size. When the backrest or knee section rises, the mattress needs to follow the changing platform geometry. A mattress that is too rigid can resist movement on either manual or electric beds. A stronger actuator should not be used to force an unsuitable mattress to bend. The mattress and platform should be designed to work together. Different models can use different side-rail systems regardless of how the mattress platform is adjusted. Possible designs include aluminum alloy folding rails and ABS rail systems depending on model. Selected hospital-bed designs may use side rails around 400 mm high relative to the platform. Once a mattress is installed, the remaining effective height above the sleeping surface becomes lower. Check locking, release, alignment and mounting. An electric five-function bed with a poor rail system is not automatically a better complete product than a simpler manual bed with well-designed rails. Hospital beds need to be moved for cleaning, maintenance and ward positioning. The caster system should therefore be evaluated regardless of whether the bed uses motors or cranks. Each caster is locked separately. This can suit beds that are moved less frequently. Selected higher-level models may use a linked braking system. This can make locking and releasing multiple casters more convenient when beds move regularly. An electric bed does not automatically require central braking, and a manual bed is not automatically limited to one specific brake configuration. The complete model specification should be checked. Where the ward mainly needs backrest and leg adjustment, a manual two-crank bed can provide a straightforward product configuration. This can make the specification easier to understand and standardize. When height adjustment is also required, the three-crank design provides another level of functionality without introducing electric actuators. This is one of the most useful comparisons for buyers. Both products may provide back, leg and height adjustment, but one uses cranks and the other uses powered controls. This single question can clarify much of the selection decision. Manual adjustment may remain practical. Electric control can reduce repeated crank operation. Not every hospital department has the same positioning requirements. Some general wards can use manual two-crank or three-crank beds where routine positioning requirements are relatively straightforward. Other wards may prefer electric three-function beds because staff adjust positions more frequently. Where more complex positioning is required, five-function electric or higher-level bed configurations can provide additional movement options. Product selection should follow the actual care specification. An extra function has value only if it will be used. Additional movements generally introduce more mechanical and electrical components. If staff will operate every adjustment repeatedly, the manual mechanism may create more work over time. Usage pattern should remain part of the decision. An electric bed requires an appropriate electrical system for powered functions. Manual beds do not rely on electrical power for their crank-driven adjustments. Some electric hospital-bed configurations can offer battery-related options, while others may not. Buyers should verify the exact electrical configuration instead of assuming all electric beds include backup power. Some electric systems may include mechanical or emergency provisions depending on the design. These features should be confirmed individually rather than treated as standard across all electric beds. Depending on configuration, motor systems can use IPX4 protection, while IPX5 can be available on selected systems. The exact rating should be confirmed for the bed supplied. A manual crank system does not contain powered actuators, so electrical protection specifications relate to a different product architecture. Manual mechanisms create mechanical operating sounds during crank use. Electric beds produce actuator and motor sound during powered movement. The quality of either system should be evaluated on the complete assembled bed. A well-designed electric bed should operate smoothly, but motors and gears still produce operating sound. Poorly aligned mechanical systems can create unwanted noise as well. During sample inspection, pay attention to scraping, clicking, strong vibration or sudden changes in operating noise. A manual bed moves according to how quickly the caregiver turns the crank. An electric bed uses the actuator's designed movement speed and control response. The caregiver can feel changes in resistance through the crank. Unexpected resistance can indicate that further inspection is needed. Buyers should watch the platform while listening to the actuator throughout the complete movement range. Manual cranks can stop wherever the caregiver stops turning, within the intended range. Electric controls allow movement to stop when the control button is released according to the system design. Do not test only fully flat and fully raised positions. Try several intermediate angles. In a showroom, turning a crank once is easy. Pressing an electric button once is also easy. The real question is what happens after hundreds or thousands of routine adjustments across the service life of a bed fleet. If a ward contains many beds, caregiver workflow can magnify small operational differences. A function that saves only a small amount of physical effort on one adjustment may become more meaningful when repeated across many beds. A manual bed with fewer electrical components can be easier to understand in settings where basic adjustment is sufficient. This is why there is no universal winner. Manual beds mainly require inspection of mechanical adjustment components. Electric beds add electrical components that may need access during service. Crank mechanisms, screw systems, pivots, linkages, rails, casters and brakes. Actuators, control box, handset, cables and power components in addition to the same mechanical areas. They simply create a more complex system that needs correct component matching and service planning. A poorly made mechanical crank can still fail to operate correctly. Build quality matters on both product types. A manual-bed spare-parts plan may focus on crank mechanisms, rail parts and caster components. An electric-bed plan may additionally need model-specific electrical components. A handset, actuator or control box should not be replaced simply because another component has a similar connector. The replacement needs to match the intended system. Crank screw length, mounting position and linkage geometry can vary between bed models. Mechanical parts are not automatically interchangeable. The main cleaning principles depend more on bed construction than drive type. However, electric beds contain additional cables and electrical components that should be considered according to the manufacturer's cleaning instructions. Crank linkages underneath the platform can create their own joints and surfaces. Product comparison should not be limited to the top view. The underside reveals much of the real design difference. Place comparable manual and electric products next to each other with the intended mattress installed. Operate the manual crank and then the electric control. Observe final angle, movement smoothness and platform stability. Look at the knee-section geometry and mattress articulation. If both products support it, operate the complete range. Check minimum height, intermediate positions and maximum height. Height-adjustable structures can feel different when fully extended. This comparison should be performed according to the manufacturer's intended operating conditions. Ask who operates the bed and how often. Rail design may have more impact on daily bedside access than the choice between electric and manual drive. A good mobility system remains important on both. Make sure the same type of mattress is not masking differences in platform geometry. “Electric” and “manual” are only two words in a much larger technical specification. It can be a practical configuration when the ward needs straightforward backrest and leg adjustment without frequent powered positioning. It provides a relatively simple product structure for basic patient-care environments. It becomes useful when the hospital also wants overall height adjustment but still prefers mechanical operation. It can suit wards where backrest, leg and height functions are used regularly and caregivers benefit from push-button adjustment. It is more suitable when the project genuinely needs additional whole-bed positioning such as Trendelenburg and reverse Trendelenburg. This is the central decision. The buyer should first define required movements and then decide whether those movements should be mechanical or powered. Product cost matters, but selecting the wrong operating system can create a bed that staff either underuse or find unnecessarily complicated. Buying the most complex electric bed for every ward can also create unnecessary product complexity. Hospitals do not always need one bed specification for every department. Different wards can use different product levels according to actual clinical workflow and positioning requirements. Once a suitable model has been selected for a particular ward type, standardizing the same frame, rail, caster and control configuration can simplify operation and parts management. A distributor does not necessarily need ten models that differ only slightly. A clearer range can use several distinct product levels. Manual two-crank hospital bed. Manual three-crank hospital bed. Electric three-function hospital bed. Electric five-function or ICU-oriented configuration. Each product has a clear reason to exist rather than competing only on small cosmetic details. A flat manual bed and flat electric bed can look very similar in catalogue photographs. Useful images should show the products in different positions. Buyers need to see: crank location, storage position and how many mechanisms are provided. This immediately communicates the different operating method. Side views help buyers compare: backrest angle, leg articulation, platform height and overall geometry. A video can demonstrate exactly how much caregiver input each system requires. Do not show only the final position. The buyer should see which button creates each function. Comparing products becomes much easier when manual and electric models use a consistent specification format. overall dimensions, mattress-platform dimensions, backrest range, leg range, height range, safe working load, rail system, caster system and adjustment method. Clearly state whether each function is: manual crank, electric actuator or another model-specific mechanism. An electric bed should be sold by what it can actually do, not merely how many motors it contains. A buyer should know exactly what each crank controls. Buyers can review additional electric and manual hospital bed configurations to compare two-crank, three-crank, three-function electric, five-function electric and higher-level patient-bed designs. Hebei Heyuan Medical Equipment has approximately 20 years of experience manufacturing hospital beds, nursing beds and related medical furniture. Our hospital-bed range includes manual two-crank beds, manual three-crank beds, electric three-function beds, electric five-function beds and other patient-care configurations. Depending on model, products can use different side rails, medical casters, braking systems, mattress platforms and adjustment mechanisms. The most useful way to think about electric vs manual hospital bed selection is to compare the same patient-care movement in two different drive systems. A manual backrest uses a crank and mechanical linkage. An electric backrest uses an actuator and control system. A manual height-adjustable bed requires mechanical operation. An electric bed changes the same general platform level through powered controls. Neither approach is automatically correct for every ward. If adjustments are relatively simple and infrequent, a manual bed can provide the required functions with a straightforward mechanical structure. If backrest, leg and height positions are changed repeatedly during daily care, electric operation can make those same movements easier to access. The decision should therefore be based on function count, adjustment frequency, caregiver workflow, frame design, rails, casters, mattress compatibility and the actual ward application—not on the idea that one technology is universally better. If you are comparing manual and electric hospital-bed configurations for a hospital project or distributor product range, please contact our team with the required functions, quantity and intended application. We can help compare suitable product configurations.When Is an Electric Hospital Bed Worth Choosing Over a Manual Model?
Start With What Both Bed Types Actually Need to Do
Manual and Electric Describe the Drive Method
Manual Hospital Bed
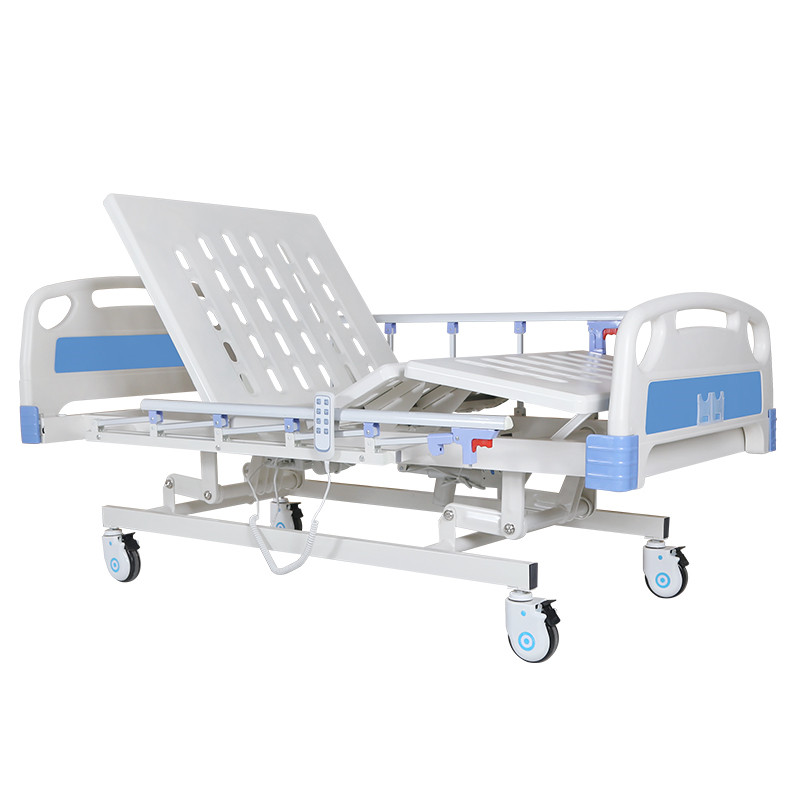
Electric Hospital Bed
The Mattress Platform Can Be Similar Even When the Drive System Is Different
Backrest Adjustment Is the Easiest Function to Compare
How Does a Manual Backrest Move?
How Does an Electric Backrest Move?
The Final Angle Is Only One Part of the Comparison
Adjustment Frequency Is One of the Most Important Differences
Leg Adjustment Follows the Same Principle
Back and Leg Functions Are Often Used Together
This Is Where Repeated Operation Becomes Noticeable
Overall Height Adjustment Creates a Larger Difference
Manual Three-Crank Beds Can Provide Height Adjustment
Electric Height Adjustment Uses a Powered Lifting System
Height Adjustment Can Be Used More Frequently on an Electric Bed
This Does Not Mean Every Hospital Needs Electric Height Adjustment
Compare Manual Two-Crank and Three-Crank Beds Separately
Manual Two-Crank Bed
Manual Three-Crank Bed
Function Count Should Be Confirmed, Not Assumed
Electric Three-Function Beds Need the Same Clarity
A Five-Function Electric Bed Adds More Positioning Capability
This Is Not an Equal Product Comparison
Compare Equivalent Function Levels First
The Crank Mechanism Is the Core of a Manual Bed
What Should Buyers Inspect on a Manual Crank?
Look Under the Bed While the Crank Is Moving
A Good Manual Bed Is a Mechanical System
Electric Beds Replace the Crank With Several Electrical Components
The Actuator Is Only One Part of an Electric Bed
Actuator Mounting Points Carry Real Force
The Control Box Coordinates the Electrical System
The Handset Changes How the Bed Is Used
Who Will Operate the Bed?
Manual Beds Keep Adjustment Control With the Caregiver
Electric Beds Can Provide Different Control Layouts
Electrical Complexity Should Match the Ward
Manual Beds Have Fewer Electrical Components
But Mechanical Components Still Require Inspection
Electric Beds Still Contain the Same Basic Mechanical Structure
Frame Construction Should Be Evaluated Independently of Drive Type
A Manual Bed Is Not Automatically Lighter-Duty
An Electric Bed Is Not Automatically Stronger
Safe Working Load Must Be Model-Specific
Load Travels Through Similar Structural Areas
What Changes Is How the Platform Moves
Mattress Compatibility Matters for Both Bed Types
Compare Mattress Platform Dimensions
Mattress Flexibility Affects Articulation
Electric Power Does Not Solve a Poor Mattress Match
Side Rails Are Also Independent of Electric or Manual Drive
Rail Height Should Be Checked With the Mattress Installed
The Rail Mechanism Should Be Evaluated Separately
Casters Matter on Both Product Types
Individual Brakes Can Be Used on Simpler Bed Configurations
Central Braking Can Improve Movement Workflow
Brake Type Is Not Determined by Motor Count
Manual Beds Can Be Easier to Specify for Basic Wards
Manual Three-Crank Beds Add More Flexibility
Electric Three-Function Beds Target the Same Core Movements With Different Operation
Ask How Often Each Function Will Be Used
If Functions Are Used Occasionally
If Functions Are Used Repeatedly
Ward Type Matters
General Wards May Use Several Bed Levels
Higher-Care Areas May Require More Powered Functions
Do Not Buy Five Functions When Three Are Enough
Do Not Choose Manual Only Because the Initial Product Looks Simpler
Power Availability Is Relevant but Should Not Be Oversimplified
Battery Backup Is Model-Specific
Manual Emergency Operation Is Also Model-Specific
Electrical Protection Should Be Checked on Electric Models
This Comparison Does Not Apply to Manual Beds in the Same Way
Noise Is Another Practical Difference
Electric Does Not Mean Silent
Manual Does Not Mean Noiseless
Listen for Abnormal Sound Rather Than Expecting Zero Sound
Movement Speed Is Different
Manual Adjustment Gives Direct Mechanical Feedback
Electric Movement Gives Visual and Audible Feedback
Intermediate Positioning Works Differently
Fine Positioning Should Be Tested on Both
Repeated Daily Use Is Where the Difference Becomes Most Obvious
Think at Ward Scale, Not Only One-Bed Scale
But Simplicity Can Also Scale Well
Maintenance Access Is Different
Manual Bed Service Areas Can Include
Electric Bed Service Areas Can Include
More Components Do Not Automatically Mean Poor Reliability
Fewer Components Do Not Automatically Mean Better Quality
Replacement Parts Differ
Compatibility Is Especially Important on Electric Parts
Manual Parts Also Need Model Matching
How Does Cleaning Differ?
Manual Beds Still Have Hard-to-Reach Mechanisms
Look at the Underside of Both Beds
What Should Buyers Compare Side by Side?
First Compare Backrest Movement
Then Compare Leg Adjustment
Then Compare Height Adjustment
Compare Frame Stability at Maximum Height
Compare Controls and Cranks
Compare Side Rails
Compare Casters and Brakes
Compare the Mattress
Compare the Complete Product, Not the Label
When Does a Manual Two-Crank Bed Make Sense?
When Does a Manual Three-Crank Bed Make Sense?
When Does an Electric Three-Function Bed Make Sense?
When Does a Five-Function Electric Bed Make Sense?
Function Need Should Determine Product Level
Do Not Start With Budget Alone
Do Not Start With “Highest Specification” Either
A Mixed Bed Fleet Can Be Logical
Standardize Within Each Intended Use
How Should Distributors Build a Product Range?
Entry Manual Level
Height-Adjustable Manual Level
Powered General-Ward Level
Higher-Function Electric Level
This Makes the Differences Easier to Explain
Product Photography Should Show the Functional Difference
Show the Cranks on Manual Models
Show the Handset and Actuators on Electric Models
Use Side-View Position Photos
Function Videos Are Even More Useful
For Manual Beds, Show a Complete Crank Adjustment
For Electric Beds, Show the Controller and Movement Together
Technical Datasheets Should Use the Same Structure
Useful Fields Include:
Do Not Hide the Drive Method Inside Marketing Language
Motor Count Should Not Replace Function Description
Crank Count Should Not Replace Function Description Either
Compare More Hospital Bed Configurations
Hospital Beds From Heyuan Medical
The Best Choice Depends on How the Bed Will Be Adjusted Every Day