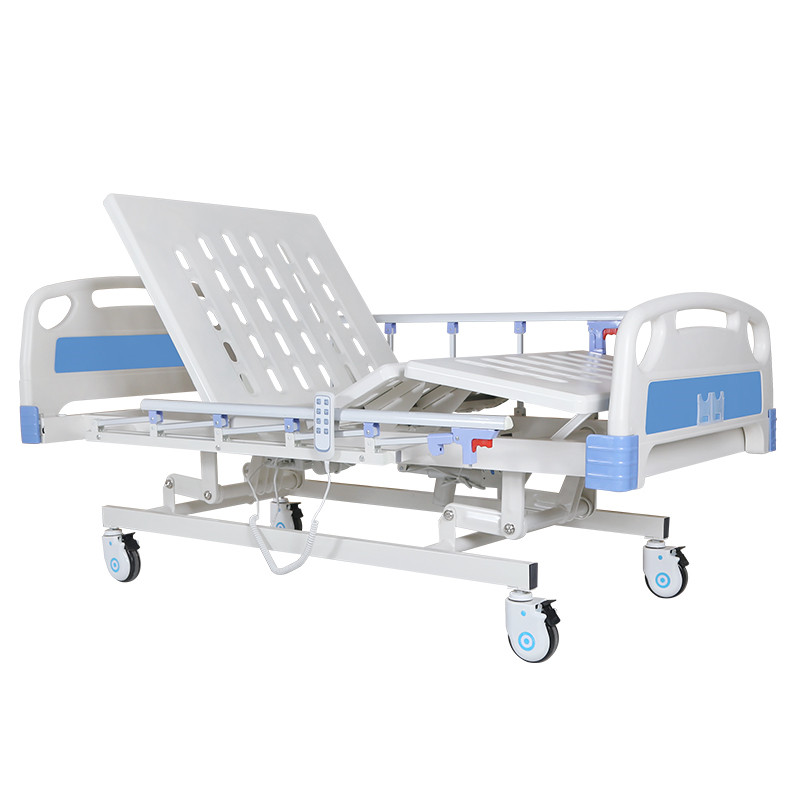


A hospital bed may have reliable motors, strong side rails, a central braking system, and an appropriate mattress. But if the mattress surface is too high or too low for the patient and the activity being performed, everyday care can still become unnecessarily difficult. A patient may struggle to sit securely at the edge. Standing may require more effort. Wheelchair transfers may become awkward. Nurses may constantly raise or lower the bed before routine care. Shorter patients may feel as though they are sliding off the mattress just to reach the floor, while taller or stronger patients may struggle to stand from a surface that has been left extremely low. This is why hospital bed height should not be treated as one fixed number. A well-designed Hospital Bed should provide an adjustment range that supports different patients and different activities rather than forcing every task to happen at the same height. Hospital bed specifications can be confusing because manufacturers may measure height from different points. If one supplier lists platform height and another lists mattress-top height, the two beds may appear similar on paper even though the patient's actual sitting height is different. When a patient sits at the edge of the mattress, being able to establish an appropriate and stable position can be important before standing or transferring. A bed that works comfortably for a tall adult may be much less suitable for a shorter elderly patient. Procurement teams should therefore evaluate the height range, not only the maximum height. Lower is not automatically better. A very low position may be useful in selected situations, but standing from an extremely low surface can require more lower-body effort. Bed height should be adjusted according to the patient's mobility and the activity being performed. Patient height is only one part of hospital bed height selection. Nurses and caregivers also work around the bed repeatedly. An electric height-adjustable bed allows staff to raise the working surface when appropriate and return the bed to another position after care. This is one of the most important concepts for buyers to understand. The practical value of a hospital bed is not that it can reach one particular height. It is that staff can adapt the bed to different situations. This is a common procurement mistake. A supplier may advertise a low platform height, but the patient does not sit directly on the steel platform. Bed platform height + mattress thickness If two beds have the same platform height but one uses a much thicker mattress, the patient will experience a different final height. Do not approve minimum bed height based on an empty bed frame. This reduces the risk of changing mattress thickness later and unintentionally changing the patient's effective bed height. Hospitals treat patients with very different body dimensions and mobility levels. A general ward bed needs enough adjustment range to serve the patient population expected to use it. A difference of several centimeters may look important in a comparison table. But the real question is whether that difference improves the intended patient-care workflow. Usable adjustment range matters more than winning a catalog comparison by a few millimeters. Bed-to-wheelchair movement is common in hospitals, rehabilitation facilities, and long-term care environments. Factors include: It allows the bed to be configured according to the individual transfer plan rather than forcing every wheelchair to adapt to a fixed bed height. The appropriate setup depends on the transfer method and patient condition. Bed adjustment should support the method selected by trained staff rather than substitute for proper patient-handling assessment. Hospital bed height also interacts with bedside equipment. Buying them independently without checking compatibility may lead to a table that cannot lower or raise far enough for some positions. Bed height is not only about the top surface. The structure underneath the bed also matters. Check: The lowest bed may still be incompatible with a particular lift if the base cannot move into the required position. A height-adjustable bed is only useful when the position is managed correctly. After the task is complete, staff may need to return it to the appropriate position according to the patient's care plan and facility procedure. A bed can provide an excellent height range, but staff training is still required to use that range effectively. This is one of the most common questions buyers ask, but it can also be misleading. Hospital beds vary by: For procurement, an adjustable range is more informative than one generic “standard hospital bed height” number. A practical bed-height worksheet can include two measurements. This helps buyers compare bed-frame specifications. This represents the height the patient actually experiences. Otherwise a later mattress change can make historical bed-height records misleading. Wheel diameter can influence the geometry of the undercarriage and overall bed design. However, buyers should not assume that a larger caster automatically means a proportionally higher minimum mattress surface. This may include: Do not calculate minimum height from individual component dimensions. Manual hospital beds can also provide height adjustment. If adjustment requires repeated crank operation, staff may use the height function differently from an electric system. For a facility where height changes occur frequently throughout the day, ease of adjustment becomes part of the procurement decision. A height motor has little operational value if the controls are inconvenient. Ask staff whether they can change bed height without walking unnecessarily around the bed or searching for the handset. Buyers usually check minimum and maximum height but rarely consider adjustment time. If routine adjustment takes too long, caregivers may be tempted to leave the bed at one compromise height. The purpose is not to choose the fastest motor possible. The goal is to confirm that movement is smooth, practical, and appropriate for routine clinical use. Height adjustment should also be evaluated mechanically. Operate the bed repeatedly through the range expected during normal use. On an adjustable medical bed, both sides of the platform should move according to the intended design. Where permitted by the manufacturer's testing procedure, evaluate movement under an appropriate representative load. Hospitals sourcing internationally should avoid assuming that one bed-height specification suits every destination market. A general ward serving many shorter elderly patients may have different practical requirements from a facility serving another population. A supplier can provide a more useful recommendation when the destination and expected patient profile are known. Procurement teams sometimes focus so heavily on minimum height that they forget the opposite end of the adjustment range. A very low minimum does not compensate for insufficient working height. Factory drawings are useful, but physical measurement provides another level of confirmation. These measurements can become part of the final production specification. In bulk production, buyers should define which dimensions are critical and how acceptable variation will be handled. Supplier and buyer should be comparing the same reference points. No. An ultra-low bed can be valuable for selected users and care environments, but lower minimum height should not automatically become the only procurement goal. A specialized low bed and a general hospital bed can serve different roles within the same facility. Standardization can simplify training, maintenance, and spare-parts management. But different departments may have different clinical workflows. The goal is not to create unnecessary bed models, but neither should procurement ignore real differences in patient use. A weak RFQ may simply say: “Electric hospital bed with height adjustment.” This leaves too much open to interpretation. This converts a marketing feature into a measurable procurement requirement. Do not simply lower the bed and write down the number. A technically impressive low position has little value if it does not improve the intended care scenario. Next, raise the bed to a realistic working level. The people who use the adjustment every day may notice usability issues that purchasing staff do not. When buyers ask, “What is the standard hospital bed height?” they are usually searching for one number that can be placed into a specification sheet. But real patient care is more complicated. A shorter patient may need a lower mattress surface to sit comfortably at the bed edge. A patient preparing to stand may require a different position. A nurse performing bedside care may need the bed raised. A wheelchair or patient lift may introduce another set of dimensional requirements. This is why the most useful hospital bed is not necessarily the model with the lowest possible minimum height. It is the bed whose adjustment range works with the actual patients, mattresses, caregivers, transfer equipment, and workflows inside the facility. For procurement teams, the lesson is simple: Do not buy “hospital bed height” as a single number. Buy an appropriate usable height range and verify it with the final mattress before mass production. During sample approval, install the exact mattress planned for the bulk order and measure floor-to-mattress-top height at both the minimum and maximum positions. Then test the bed with two scenarios: a shorter patient sitting at the edge and a caregiver performing bedside work. If the bed only performs well in one scenario, the published height range may not match the facility's real operating needs. You can review our Factory information to learn more about hospital bed production, assembly, dimensional inspection, and function testing. If you are purchasing hospital beds for hospitals, healthcare projects, distributors, or government tenders, Contact Us to discuss hospital bed height ranges, mattress configurations, electric adjustment systems, patient transfer requirements, and suitable bed models.If a Patient's Feet Cannot Reach the Floor, the Bed Height Is Not a Small Detail
First Understand Which “Hospital Bed Height” You Are Comparing
A Specification May Refer To:
These Numbers Are Not Interchangeable
Problem 1: A Bed That Is Too High Can Leave the Patient's Feet Hanging
A Bed That Is Too High May Cause the Patient To:
Shorter Patients Are Particularly Important to Consider
Problem 2: A Bed That Is Too Low Can Make Standing Much Harder
The Patient May Need More Effort From:
The Lowest Possible Bed Position Is Not Necessarily the Best Transfer Position
Problem 3: Caregivers May Spend the Entire Shift Bending Over the Mattress
Daily Tasks Can Include:
A Fixed Low Working Height Can Increase Unnecessary Bending
One Bed Height Cannot Optimize Every Activity
The Best Height for Sleeping May Be Different From the Best Height for:
Think in Terms of a Height Range
Problem 4: Mattress Thickness Can Make a “Low Bed” Much Higher Than Expected
The Real Sitting Height Is Approximately:
A 150 mm Mattress Changes the Result
Always Evaluate the Bed With the Final Mattress Installed
During Sample Testing:
Write the Complete Configuration Into the Purchase Specification
Problem 5: A Hospital Bed May Be Low Enough for One Patient but Too High for Another
Consider:
There Is No Universal Patient Height
Do Not Choose the Minimum Height From a Catalog Number Alone
Ask:
The Lowest Number Is Not Automatically the Best Specification
Problem 6: Wheelchair Transfers Become Awkward When the Two Surfaces Are Poorly Matched
A Large Height Difference Can Make Transfer Planning More Complicated
Adjustable Height Provides More Flexibility
Do Not Assume “Same Height” Is Always the Correct Transfer Setup
Different Transfers May Use:
Follow the Individual Transfer Plan
Problem 7: Overbed Tables May No Longer Fit Correctly
An Overbed Table Needs Sufficient Adjustment Range To Work When the Bed Is:
Check the Bed and Table Together
Problem 8: Patient Lift Compatibility Can Be Affected by the Bed Base
A Mobile Patient Lift May Need Clearance Under the Bed for Its Base
Do Not Evaluate Lift Compatibility From Bed Height Alone
Problem 9: Staff May Forget to Return the Bed From Working Height
During Nursing Care, the Bed May Be Raised for Better Working Access
Workflow Matters as Much as Mechanical Capability
What Is a Standard Hospital Bed Height?
There Is No Single Height That Solves Every Situation
Compare Minimum and Maximum Platform Height Instead
Platform Height and Mattress-Top Height Should Both Appear in Your Evaluation
Measurement A: Floor to Mattress Platform
Measurement B: Floor to Top of Final Mattress
Keep Both Numbers
Do Larger Casters Increase Hospital Bed Height?
The Complete Lifting Mechanism Determines the Final Height Range
Compare the Actual Finished Bed
What About Manual Hospital Beds?
But Consider How Frequently Staff Will Change the Height
Usage Frequency Matters
Electric Height Adjustment Should Be Easy to Reach
Depending on the Model, Controls May Be Located On:
Test the Controls in a Real Care Position
How Fast Should a Hospital Bed Raise and Lower?
A Very Slow Height Change Can Affect Whether Staff Actually Use the Function
Test a Full Height Cycle During Sample Approval
Listen to the Bed During Height Adjustment
During Repeated Up-and-Down Cycles, Check for:
A Function Test Should Be More Than One Button Press
Check Whether the Bed Remains Level While Raising and Lowering
During Inspection, Observe:
Do Not Approve a Sample Only While Unloaded
Minimum Height Is Particularly Important for Shorter Patient Populations
Patient Populations Differ
Give the Manufacturer Patient-Use Context
Maximum Height Matters to Nurses Too
A Sufficient Working Height May Help During:
Evaluate Both Ends of the Range
Measure the Height Range With the Bed Fully Assembled
During Sample Inspection:
Record the Approved Values
Do Not Forget Manufacturing Tolerance
For Bed Height, Ask the Supplier:
Consistent Measurement Prevents Disputes
Should Hospitals Always Buy Ultra-Low Beds?
Buyers Should Balance:
Choose the Bed for the Intended Use
Should Every Ward Use the Same Bed Height Range?
Consider the Needs of:
Standardize Where Practical, Specialize Where Necessary
What Bed Height Information Should Appear in an RFQ?
A Better RFQ Can Specify:
Then Verify the Final Mattress-Top Height on the Sample
Ask the Manufacturer These 12 Questions About Hospital Bed Height
Test the Lowest Position With a Realistic Patient Scenario
During Evaluation, Ask:
Numbers Need Context
Test the Maximum Position With a Caregiver Scenario
Ask a Nurse or Caregiver to Simulate:
Get Staff Feedback Before Bulk Production
Hospital Bed Height Checklist Before Ordering
Common Hospital Bed Height Buying Mistakes
The Right Hospital Bed Height Is Not One Number — It Is the Ability to Adapt
Expert Tip