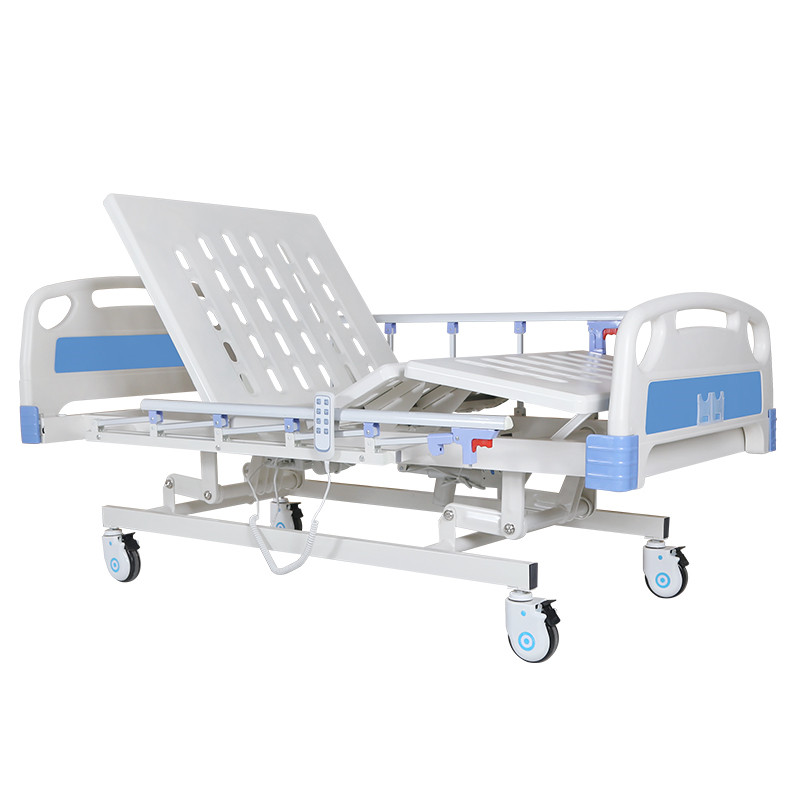


A patient rolls onto their side. The hospital bed moves slightly. They sit up. The bed shakes again. A nurse pushes on the mattress edge and hears a click from underneath. Before long, staff begin describing the bed as: “Loose.” “Unstable.” “The frame is probably damaged.” Sometimes a structural problem really is responsible. But a hospital bed can feel unstable because of several different components: the floor, casters, brake system, detachable head or footboard, frame connections, moving platform sections, assembly hardware or damage after transport. That means replacing the complete frame before locating the actual movement can be expensive and unnecessary. When inspecting a Hospital Bed, start with one question: Which part of the bed is actually moving? Start outside the bed. A perfectly normal bed can rock if one caster is standing on a lower section of floor, damaged tile, floor joint or uneven surface. With the bed unloaded where appropriate, observe whether all casters appear to make consistent contact with the floor. Then move the bed to another flat area and repeat the check. If the wobble disappears after relocation, investigate the floor before replacing bed components. A hospital bed may have four casters that look almost identical while one behaves differently under load. Look for: A single abnormal corner can make the entire bed feel unstable. A partially engaged brake can create a confusing symptom. The bed may not roll freely across the room, but it can still shift slightly when the patient moves. After engaging the brake according to the bed instructions, apply controlled pressure to the frame and observe whether the casters remain stable. If the braking behavior is abnormal, remove the bed from normal service until the cause is appropriately assessed. Detachable head and footboards are useful for cleaning, maintenance and emergency access. But if their mounting interfaces become loose, the sound and movement can make the entire bed seem unstable. With the bed stationary, gently check whether movement comes from: A loose detachable board is very different from a cracked main frame. The patient lies on an articulated mattress platform rather than directly on the base chassis. Movement between these structures can sometimes be mistaken for complete frame instability. Look for unexpected play around: Compare the movement with another identical bed if one is available. If the bed was recently assembled, repaired or reassembled after transport, start with the areas that were disturbed. Was the bed: A problem that begins immediately after service or transport should be investigated in that context. Loose, incorrect or missing fasteners should be addressed according to the manufacturer's service procedure rather than tightened randomly. Staff often test bed stability by holding the side rail and pushing. But the side rail itself may contain normal operating clearance or may have a separate mounting problem. Hold the fixed bed structure and observe whether the rail moves independently. If the rail mounting or locking mechanism is abnormal, treat it as a rail problem rather than assuming the complete chassis is loose. This is one of the most useful diagnostic clues. Does the instability appear when: If the wobble appears only in one position, focus on the mechanisms and joints involved in that configuration. Hospital beds are repeatedly moved through corridors, elevators, doorways and loading areas. An impact can affect a caster mount, lower frame member or connection point without creating an obvious defect at mattress level. Look for: If structural damage is suspected, stop normal use and arrange an appropriate inspection. Only after the simpler causes are separated should the main welded frame become the focus. Look for: A confirmed structural problem requires appropriate technical evaluation and should not be treated as a routine tightening issue. Think first about floor contact and the four caster positions. If pressing one corner causes the opposite corner to move, inspect floor contact and lower-frame geometry. This points more strongly toward caster or braking behavior than mattress-platform movement. Focus above the chassis. Check detachable boards, board posts and the corresponding end of the frame. Try to locate the sound rather than guessing from above the mattress. Record the bed from the side while controlled movement is reproduced briefly. This removes one variable immediately. Start with a repeatable configuration rather than testing random positions. Label them mentally as: Head Left – Head Right – Foot Left – Foot Right. Identify which corner begins the movement. This helps distinguish removable-board movement from chassis movement. If the facility owns multiple units of the same model, side-by-side comparison is extremely useful. Compare actual visible movement. If you see a crack, bent frame member, displaced caster mount or abnormal structural movement, arrange appropriate inspection before returning the bed to service. Random tightening can hide the original problem or create incorrect assembly conditions. A repair that addresses only the visible crack may fail again if the underlying cause is distortion, repeated mechanical binding, impact damage or another structural issue. Find the abnormal corner first. A targeted diagnosis can reduce unnecessary parts replacement. A bed can successfully raise the backrest and still feel structurally poor. Test the bed: Consistency matters in project procurement. If one bed feels noticeably different, investigate before shipment. Many problems are located below the level buyers normally photograph. Check caster mounts, lower-frame members, connections and moving structures. Production inspection should evaluate the completed product, not only individual components. You can review our Factory information when evaluating hospital-bed assembly and inspection capabilities. When a bed wobbles, do not begin by guessing which expensive component to replace. Begin at the floor. Then check each caster. Then the brake system. Then removable boards. Then the mattress platform. Then assembly points. Then impact history. Only after those factors are separated should the main frame become the primary suspect. The fastest way to solve an unstable-bed complaint is to locate the first point of movement instead of treating the whole bed as one component. Film the bed from floor level rather than standing beside it. Keep all four caster areas visible if possible and ask a second person to apply light controlled pressure to each corner in sequence. Slow playback often reveals that one caster mount, detachable board or platform connection begins moving before the rest of the bed. That first movement point is usually much more useful for diagnosis than the loudest sound. You can explore our Hospital Bed range for hospital projects requiring stable frames, practical positioning functions, medical casters and different manual or electric configurations. If you are comparing hospital beds for a project or troubleshooting repeated instability across several units, Contact Us to discuss bed structure, caster systems, assembly requirements and project inspection needs.If the Bed Shakes Every Time the Patient Moves, Do Not Assume the Whole Frame Is Bad
10 Things to Check When a Hospital Bed Feels Wobbly or Unstable
1. Check Whether the Floor Is Flat
Watch All Four Casters
2. Check Whether One Caster Is Sitting Differently From the Others
Compare the Four Corners
3. Check Whether the Brake System Is Fully Engaged
Do Not Judge the Brake Only by Pedal Position
4. Check Whether the Movement Is Coming From the Headboard or Footboard
Hold the Main Frame and Board Separately
5. Check Whether the Mattress Platform Is Moving Inside the Main Frame
Observe the Backrest and Leg Sections
6. Check for Loose or Missing Assembly Hardware
Ask What Happened Before the Wobble Started
7. Check Whether a Side Rail Is Creating the Feeling of Instability
Separate Rail Movement From Frame Movement
8. Check Whether the Wobble Appears Only at Certain Bed Positions
Compare Several Approved Positions
9. Check for Impact or Transport Damage Around the Lower Frame
Inspect the Corners and Lower Chassis
10. Check Whether the Main Frame Actually Has Abnormal Movement
Watch Structural Joints While Controlled Pressure Is Applied
The Type of Wobble Can Tell You Where to Look
The Whole Bed Rocks Diagonally
Compare Opposite Corners
The Bed Shifts Sideways but Does Not Rock
Observe the Wheels While Pressure Is Applied
The Mattress Platform Moves but the Base Stays Still
Inspect Platform Connections and Moving Sections
Only the Head or Foot End Feels Loose
The Bed Clicks Only When the Patient Turns
A Low-Angle Video Can Help
Use This Simple Four-Corner Test Before Replacing Parts
Step 1: Place the Bed on a Known Flat Surface
Step 2: Set the Bed in a Standard Approved Position
Step 3: Observe Each Corner Separately
Apply Gentle Controlled Pressure
Step 4: Repeat With the Headboard and Footboard Held Separately
Step 5: Compare With an Identical Bed
Do Not Compare Only by Sound
Do Not Make These Four Mistakes With an Unstable Hospital Bed
Do Not Keep the Bed in Patient Use if Structural Damage Is Suspected
Do Not Tighten Every Bolt You Can See
Follow the Manufacturer's Service Information
Do Not Weld a Cracked Frame Without Understanding Why It Cracked
Do Not Replace All Four Casters Because One Corner Feels Loose
Hospital Buyers Should Test Stability Before Accepting a Bulk Order
Do Not Inspect Only the Electric or Manual Functions
Add a Stability Check to Final Inspection
Test More Than One Finished Bed
Compare Several Units From the Same Order
Inspect the Lower Frame, Not Just the Mattress Platform
Look Under the Bed
Ask How the Bed Was Tested After Final Assembly
Hospital Bed Stability Inspection Checklist
Floor and Caster Area
Frame and Platform
Removable Components
History
12 Questions Buyers Should Ask About Hospital Bed Frame Stability
Frame Construction
Assembly Control
Replacement Parts
A Hospital Bed Should Feel Stable Before the Patient Ever Lies on It
Expert Tip